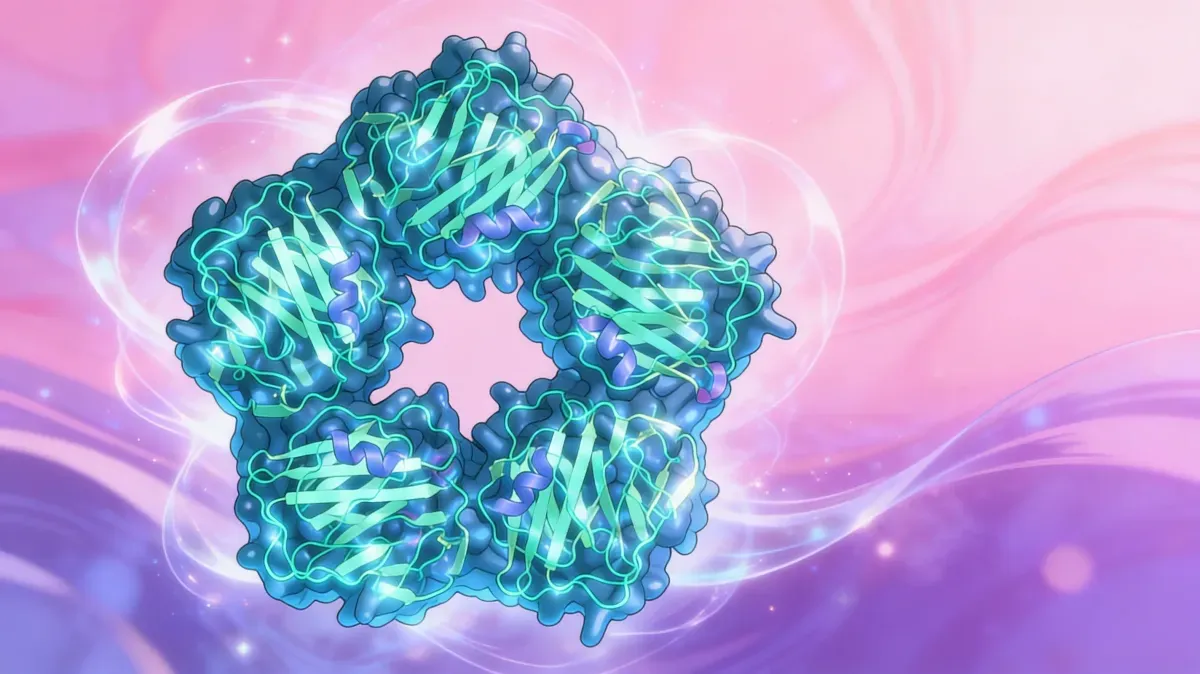
hs-CRP: The inflammation marker that predicts biological aging
Discover what hs-CRP reveals about your biological age, why chronic inflammation accelerates aging, and 7 proven strategies to lower your levels naturally.
Your blood tests came back “normal,” but your body could be aging faster than you think. The culprit? A protein most doctors barely glance at — and it might be the single most important number on your lab report for predicting how long you’ll live.
High-sensitivity C-reactive protein (hs-CRP) is not just another cardiovascular risk marker. It’s a practical readout of the chronic, low-grade inflammation that silently accelerates many aspects of biological aging — from arterial stiffness to cognitive decline. Scientists call this process inflammaging, and it’s now considered one of the central drivers of age-related disease.
The good news: hs-CRP is one of the most modifiable biomarkers in existence. In this article, you’ll learn exactly what it measures, why it matters for your biological age, and how to bring it down with evidence-based strategies.
For a lab-report reference page with ranges, aliases, and SuperAge context, see the hs-CRP biomarker guide.
What you’ll learn:
- What hs-CRP measures and how it differs from standard CRP
- Why chronic inflammation is the hidden engine of biological aging
- The optimal hs-CRP range for longevity (it’s lower than you think)
- 7 proven strategies to reduce hs-CRP naturally
What is hs-CRP?
C-reactive protein (CRP) is a substance produced by the liver in response to inflammation. When your body detects tissue damage, infection, or chronic stress, CRP levels rise — sometimes dramatically.
Quick definition: hs-CRP (high-sensitivity C-reactive protein) is a blood test that detects very low levels of systemic inflammation, measuring concentrations as low as 0.1 mg/L — making it the gold standard for assessing chronic, low-grade inflammation linked to aging and disease.
hs-CRP vs standard CRP: what’s the difference?
The standard CRP test measures levels in a broad range (typically 10–1,000 mg/L) and is used to detect acute inflammation — infections, injuries, autoimmune flares. It’s like a fire alarm: it goes off when the building is already burning.
The hs-CRP test is far more sensitive. It detects levels between 0.1 and 10 mg/L, picking up the low-grade “smoldering” inflammation that doesn’t produce symptoms but quietly damages your tissues over years and decades.
| Feature | Standard CRP | hs-CRP |
|---|---|---|
| Detection range | 10–1,000 mg/L | 0.1–10 mg/L |
| Primary use | Acute infections, trauma | Chronic inflammation, CV risk |
| Sensitivity | Low | Very high |
| Relevance to aging | Minimal | Critical |
Why hs-CRP matters for your health
According to the American Heart Association and the CDC, hs-CRP stratifies cardiovascular risk into three tiers:
- < 1.0 mg/L — Low risk
- 1.0–3.0 mg/L — Average risk
- > 3.0 mg/L — High risk
For a detailed breakdown of all three threshold systems — lab normal range, AHA/CDC bands, and longevity-aligned targets — see our hs-CRP normal range guide. Newer cardiovascular guidance also treats hs-CRP ≥2 mg/L as a risk-enhancing factor when preventive therapy decisions are uncertain, while the USPSTF still cautions that hs-CRP should not be used as a stand-alone screening shortcut for every asymptomatic adult.
But cardiovascular risk is only part of the story. Research published in Immunity & Ageing shows that elevated hs-CRP in older adults is independently associated with higher all-cause mortality — meaning it predicts death from any cause, not just heart disease. A 2022 cohort study of oldest-old adults in Chinese longevity regions found that those with the lowest hs-CRP levels had significantly longer lifespans.
The science behind hs-CRP and aging
How chronic inflammation damages your body
When inflammation is acute — a cut, a cold, a sprained ankle — CRP spikes, does its job, and goes back down. That’s healthy. The problem begins when inflammation never fully resolves.
Chronic low-grade inflammation creates a persistent state of immune activation. Your body produces a constant stream of pro-inflammatory cytokines (IL-6, TNF-alpha, IL-1beta) that trigger CRP production in the liver. Over time, this leads to:
- Endothelial damage — the inner lining of blood vessels erodes, promoting atherosclerosis
- Insulin resistance — inflammatory signaling disrupts glucose metabolism
- Mitochondrial dysfunction — energy production in cells declines
- Telomere shortening — inflammation accelerates chromosomal aging
- Neuroinflammation — brain tissue accumulates damage
This process is so central to aging that researchers coined the term inflammaging — the intersection of chronic inflammation and biological aging, and one of the 12 hallmarks of aging driving biological age acceleration. It is a defining feature of immune system aging that also underlies the surge in autoimmune diseases with age. Environmental exposures amplify this cascade: the CARDIA study found that every 5 μg/m³ increase in long-term PM2.5 exposure raised hs-CRP by 4% independent of lifestyle factors — making chronic air pollution a direct driver of the inflammaging that elevated hs-CRP reflects.
One important 2026 nuance: hs-CRP is best treated as a downstream signal, not proof that CRP itself is the causal aging switch. A Mendelian randomization study using genetic instruments from more than 750,000 people found opposing causal signals for the IL-6 pathway — higher IL-6 was linked to higher mortality, while higher soluble IL-6 receptor was linked to lower mortality — but found no significant causal effect for CRP itself. In practice, that makes hs-CRP a valuable dashboard light: if it is persistently high, look upstream for visceral fat, infection, sleep debt, insulin resistance, periodontal disease, environmental exposure, or chronic inflammatory disease.
hs-CRP and biological age: the PhenoAge connection
Here’s where hs-CRP becomes uniquely important: it’s one of the 9 biomarkers used in the PhenoAge algorithm, one of the most validated methods for calculating biological age from blood tests.
Developed by Morgan Levine at Yale School of Medicine in 2018, PhenoAge uses these biomarkers:
| # | Biomarker | What it reflects |
|---|---|---|
| 1 | Albumin | Liver function, nutrition |
| 2 | Creatinine | Kidney function |
| 3 | Glucose | Metabolic health |
| 4 | hs-CRP | Systemic inflammation |
| 5 | Lymphocyte percentage | Immune function |
| 6 | MCV | Red blood cell size |
| 7 | RDW | Red cell variability |
| 8 | Alkaline phosphatase | Liver and bone metabolism |
| 9 | White blood cells | Immune activation |
Among these, hs-CRP is one of the most actionable inputs because the PhenoAge formula includes CRP as a log-transformed inflammation term and because hs-CRP often responds to lifestyle, metabolic, dental, and medical drivers. To see how hs-CRP fits within a complete longevity testing strategy — including optimal ranges for all 24 biomarkers — read the complete blood work guide for longevity.
Lowering hs-CRP from a clearly elevated range toward below 1.0 mg/L can improve calculated PhenoAge meaningfully, especially when it happens alongside better glucose, RDW, albumin, kidney, and immune markers. The safer interpretation is directional: falling hs-CRP is a strong sign that the inflammatory load feeding the age calculation is improving, not proof that CRP alone “reversed aging.”
What the longevity research says
The evidence linking persistent inflammation to poorer aging outcomes is strong, but the most careful reading is: low and stable hs-CRP is a favorable signal; high or rising hs-CRP is a risk flag.
- Oldest-old cohorts: A 2022 study in Chinese longevity regions found that elevated hs-CRP was associated with higher all-cause mortality among the oldest-old. Low hs-CRP is favorable, but it is not a stand-alone longevity guarantee.
- UK Biobank proteomics (2025): A plasma proteomics analysis of 51,904 participants measured 2,923 proteins and identified 227 proteins associated with aging-related phenotypes. Inflammation and regeneration pathways were notably implicated, supporting multi-marker inflammaging assessment rather than CRP-only interpretation.
- Dynamic hs-CRP tracking (2024): A nationwide prospective cohort study with Mendelian randomization found that sustained elevations in hs-CRP over time carried higher mortality risk than a single elevated reading — reinforcing the value of tracking hs-CRP trends, not just isolated snapshots.
- hs-CRP/HDL-C ratio (2025): A Frontiers in Immunology study found that participants in the highest quartile of the hs-CRP to HDL-C ratio had a 122% higher risk of sarcopenia compared to those in the lowest quartile — linking inflammatory-metabolic status to muscle loss. A second 2025 Frontiers in Endocrinology analysis extended the signal to cardiovascular-kidney-metabolic (CKM) syndrome, where the hs-CRP/HDL-C ratio independently predicted all-cause mortality across CKM stages 1-4.
- Causal nuance (2026): A Mendelian randomization study in Aging found no significant causal effect for CRP itself, while the IL-6 pathway showed opposing causal signals. This supports using hs-CRP as a monitoring marker while addressing upstream inflammatory drivers.
- Longevity-Inflammation Index (2026): A January 2026 framework published in Nutrients proposed combining hs-CRP with IL-6, TNF-α, and microbiome-derived markers into a single Longevity-Inflammation Index (L-II) — moving the field from single-marker testing toward multi-axis inflammaging assessment.
7 proven ways to lower hs-CRP naturally
1. Adopt an anti-inflammatory diet
Why it works: The Mediterranean diet is the most extensively studied dietary pattern for reducing systemic inflammation. It’s rich in polyphenols — including resveratrol and quercetin, both of which block NF-kB and lower CRP in human trials — omega-3 fatty acids, and fiber — all of which down-regulate pro-inflammatory gene expression. For a complete framework covering the specific foods, mechanisms, and meal strategies, see our guide to the anti-inflammatory diet for longevity.
How to do it:
- Prioritize fatty fish (salmon, sardines, mackerel) 2–3 times per week
- Use extra virgin olive oil as your primary cooking fat
- Eat 5+ servings of colorful fruits and vegetables daily
- Include nuts, seeds, and legumes regularly
- Drink green tea or matcha daily — EGCG directly inhibits NF-κB and is associated with lower CRP in long-term drinkers
- Minimize ultra-processed foods, refined sugars, and seed oils
Expected results: A 2025 systematic review of randomized trials found that Mediterranean-diet interventions significantly improved hs-CRP, IL-6, and IL-17 compared with control diets. The exact hs-CRP change varies by baseline inflammation, adherence, and intervention length, and hs-CRP sometimes lags behind other inflammatory markers — give it 12–16 weeks before judging a protocol as ineffective.
2. Optimize omega-3 intake
Why it works: EPA and DHA — the omega-3 fatty acids found in fish oil — directly inhibit the production of pro-inflammatory cytokines (IL-6, TNF-alpha) that drive CRP production. Critically, the ratio between omega-6 and omega-3 matters as much as absolute intake — learn why in our guide to the omega-6:omega-3 ratio and inflammation.
How to do it:
- Target 2–3 g/day of combined EPA+DHA from food or supplementation
- Prioritize EPA-dominant sources for inflammation reduction
- Get an Omega-3 Index test — aim for 8–12%
Expected results: A 2025 dose-response meta-analysis found that EPA+DHA supplementation can reduce CRP in people with cardiometabolic disorders, with clinically meaningful reductions around 1,200 mg/day in that population. Higher baseline CRP levels tend to see the greatest reductions, but more omega-3 is not automatically better if your Omega-3 Index is already adequate.
3. Maintain a healthy body composition
Why it works: Adipose tissue (especially visceral fat) is not inert storage — it’s an active endocrine organ that produces inflammatory cytokines. Excess body fat is one of the strongest drivers of elevated hs-CRP.
How to do it:
- Focus on gradual, sustainable fat loss — even losing 11 lbs (5 kg) produces measurable CRP reductions
- Prioritize visceral fat reduction through exercise and dietary changes
- Monitor waist circumference: under 40 inches (102 cm) for men, under 35 inches (89 cm) for women
Expected results: Weight loss of 5–10% of body weight typically reduces CRP by 25–40%. The effect is dose-dependent — more fat loss equals greater CRP reduction.
4. Exercise consistently (but don’t overtrain)
Why it works: Regular moderate exercise has a powerful anti-inflammatory effect, mediated by the release of myokines (anti-inflammatory molecules produced by working muscles) and the reduction of visceral fat.
How to do it:
- Aim for 150–300 minutes of moderate aerobic exercise per week
- Include 2–3 resistance training sessions per week
- Walking at a brisk pace counts — you don’t need extreme workouts
- Watch for signs of overtraining, which paradoxically increases inflammation
Expected results: Regular exercisers have 20–40% lower CRP levels than sedentary individuals. Effects begin within 2–4 weeks of consistent training.
5. Prioritize sleep quality
Why it works: Sleep deprivation triggers a pro-inflammatory cascade. Even one night of poor sleep raises IL-6 and TNF-alpha levels, and chronic sleep debt creates sustained elevations in hs-CRP.
How to do it:
- Target 7–9 hours of quality sleep per night
- Maintain consistent sleep and wake times — even on weekends
- Keep your bedroom cool (65–68 °F / 18–20 °C), dark, and quiet
- Avoid screens for 60 minutes before bed
Expected results: Improving sleep from 5–6 hours to 7–8 hours nightly can reduce CRP by 15–25% within 4 weeks.
6. Manage chronic stress
Why it works: Psychological stress activates the hypothalamic-pituitary-adrenal (HPA) axis, elevating cortisol chronically. While acute cortisol is anti-inflammatory, chronic elevation paradoxically promotes inflammation through glucocorticoid resistance — the immune system stops responding to cortisol’s calming signals.
How to do it:
- Practice daily stress management: meditation, breathwork, or yoga (even 10 minutes)
- Track your heart rate variability (HRV) — a reliable proxy for stress-recovery balance
- Build recovery days into your training schedule
- Cultivate social connections — loneliness is independently pro-inflammatory
- Try gratitude journaling — clinical studies link regular practice to reductions in hs-CRP, IL-6, and TNF-α
Expected results: Mindfulness-based stress reduction programs have been shown to lower CRP by 15–20% over 8 weeks.
7. Address hidden infection and dental health
Why it works: Chronic low-grade infections — particularly periodontal (gum) disease — are a frequently overlooked driver of elevated hs-CRP. The oral microbiome directly communicates with systemic immune function. More broadly, gut health is a primary driver of systemic hs-CRP: leaky gut allows bacterial endotoxins (LPS) into the bloodstream, triggering the chronic NF-κB activation that elevates CRP.
How to do it:
- Visit your dentist regularly (at least twice yearly)
- Floss daily — periodontal pockets harbor bacteria that produce systemic inflammation
- If hs-CRP is persistently elevated despite lifestyle changes, investigate potential chronic infections
Expected results: Treating periodontal disease has been shown to reduce CRP by 0.5–1.0 mg/L, sometimes shifting patients from the high-risk to the average-risk category.
How to track and measure hs-CRP
Getting tested
hs-CRP is available through any standard blood panel — you simply need to request the high-sensitivity version. Many standard metabolic panels don’t include it automatically, so ask your doctor specifically for “hs-CRP” or “high-sensitivity C-reactive protein.”
Interpreting your results
| hs-CRP Level | Risk Category | What It Means |
|---|---|---|
| < 0.5 mg/L | Optimal for longevity | Very low inflammation — associated with biological youth |
| 0.5–1.0 mg/L | Low risk | Good. Minor room for improvement |
| 1.0–3.0 mg/L | Average risk | Moderate chronic inflammation — actionable |
| 3.0–10.0 mg/L | High risk | Significant chronic inflammation — lifestyle changes urgent |
| > 10.0 mg/L | Acute inflammation | Likely infection, injury, or flare — retest in 2–4 weeks |
Important nuances:
- A single reading above 10 mg/L usually reflects acute illness, not chronic risk. Always retest after 2–4 weeks.
- hs-CRP can fluctuate 30–40% between measurements. Track it over time, not as a single snapshot.
- For reliable trending, test every 3–6 months under similar conditions (fasting, no recent illness or intense exercise). For a complete framework on how to build your longevity blood panel — including hs-CRP alongside the full PhenoAge set and metabolic markers — see our dedicated testing guide.
Key metrics to monitor alongside hs-CRP
| Metric | Why It Matters | Optimal Range |
|---|---|---|
| Fasting insulin | Insulin resistance drives inflammation | < 5 μIU/mL |
| NLR (neutrophil-to-lymphocyte ratio) | Another inflammation marker from CBC | < 2.0 |
| HbA1c | Glycation and metabolic inflammation | < 5.4% |
| Ferritin | Iron overload increases oxidative stress | 30–100 ng/mL |
| Omega-3 index | Anti-inflammatory fatty acid status | 8–12% |
| HRV | Autonomic nervous system balance | Age-dependent — higher is better |
Serum selenium is another marker worth including: as the key activator of glutathione peroxidase, adequate selenium status directly reduces the oxidative burden that drives hs-CRP elevation. See our guide on selenium and antioxidant defense for testing ranges and interpretation.
How SuperAge helps you track inflammation and biological age
Monitoring hs-CRP and its impact on your biological age shouldn’t require spreadsheets and manual calculations. SuperAge makes the process effortless.
Automatic biomarker recognition
Upload a photo of your blood test results, and SuperAge’s AI instantly recognizes over 40 biomarkers — including hs-CRP, albumin, creatinine, glucose, and every other PhenoAge parameter. No manual data entry required.
PhenoAge calculation built in
SuperAge automatically calculates your PhenoAge biological age using the validated Levine algorithm. You’ll see exactly how your hs-CRP level — alongside 8 other biomarkers — translates into your biological age estimate.
Track inflammation over time
Each time you add new blood work, SuperAge tracks how your hs-CRP and biological age change. You’ll see whether your anti-inflammatory lifestyle is actually working, with clear trend visualizations that show progress over months and years.
Personalized insights
SuperAge doesn’t just display numbers — it highlights which biomarkers are pulling your biological age up and which are protecting you. If hs-CRP is your weakest link, you’ll know immediately and can focus your efforts where they matter most.
When hs-CRP is high only once, confirm the signal with the repeat-test decision guide before interpreting it as chronic inflammaging.
Frequently asked questions
What is a good hs-CRP level for longevity?
For longevity optimization, aim for an hs-CRP below 0.5 mg/L. While the American Heart Association considers anything below 1.0 mg/L as “low risk” for cardiovascular events, longevity-oriented tracking usually treats 0.5–1.0 mg/L as good and below 0.5 mg/L as excellent. The lower, the better only when it reflects healthy living and low inflammatory burden — not immunosuppression, acute immune suppression, or lab timing after illness.
Is hs-CRP the same as CRP?
They measure the same protein (C-reactive protein), but the hs-CRP test is far more sensitive. Standard CRP detects levels above 10 mg/L and is used for acute illness. The hs-CRP test detects levels as low as 0.1 mg/L, making it essential for assessing the chronic, low-grade inflammation that drives biological aging. Always request the “high-sensitivity” version.
Can hs-CRP change quickly?
Yes. hs-CRP is one of the most responsive biomarkers to lifestyle changes. Dietary improvements, regular exercise, weight loss, and stress management can reduce hs-CRP by 20–40% within 8–12 weeks. However, acute events (illness, injury, intense exercise) can spike it temporarily — always retest after recovery before drawing conclusions.
Does hs-CRP affect your PhenoAge biological age?
Yes. hs-CRP is one of the 9 biomarkers in the PhenoAge algorithm, and because CRP enters the formula as an inflammation term, moving from a clearly elevated value toward a low-risk range can reduce calculated biological age. Interpret that as an improvement in inflammatory risk burden, not as proof that CRP itself is the only causal lever.
What causes hs-CRP to be elevated if I’m otherwise healthy?
Common hidden causes include: visceral fat (even at a “normal” BMI), poor sleep quality, chronic stress, periodontal disease, low omega-3 intake, and excess refined sugar consumption. Chronic endocrine disruptor exposure — from BPA in food containers, PFAS in cookware and water, and phthalates in personal care products — is an underrecognized driver of persistent low-grade inflammation that elevates hs-CRP through thyroid interference, insulin resistance, and direct immune activation. It’s also worth screening for subclinical infections and insulin resistance if hs-CRP remains elevated despite lifestyle improvements.
Are there medications that lower hs-CRP for high-risk patients?
Yes. Low-dose colchicine (0.5 mg daily) was FDA-approved in 2023 specifically for reducing cardiovascular event risk via its anti-inflammatory action — it lowers hs-CRP and IL-6 by inhibiting the NLRP3 inflammasome. Statins also reduce hs-CRP independently of LDL lowering, and the CLEAR-Outcomes trial (2023) showed that bempedoic acid likewise reduces CRP in statin-intolerant patients. These options are reserved for high-risk patients under medical supervision — for most people, lifestyle measures remain the first line.
Key takeaways
- hs-CRP tracks inflammaging: It is a practical downstream signal of chronic, low-grade inflammatory load, not proof that CRP itself is the causal aging switch
- It’s a useful PhenoAge input: One of the 9 biomarkers in the PhenoAge biological age formula, and one that often improves when upstream inflammatory drivers improve
- Optimal is below 0.5 mg/L: The standard “low risk” threshold of 1.0 mg/L is useful clinically, while longevity tracking usually treats below 0.5 mg/L as excellent when achieved through healthy physiology
- It’s highly modifiable: Diet, exercise, omega-3 status, sleep, stress management, dental health, and metabolic health can reduce hs-CRP over weeks to months
- Track it regularly: Test every 3–6 months and use SuperAge to see how it impacts your biological age over time
Start lowering your inflammation today
Chronic inflammation doesn’t announce itself with symptoms. It works silently, year after year, aging your body from the inside. The only way to know where you stand is to measure — and the only way to improve is to track your progress.
Ready to take control? Download SuperAge and start tracking hs-CRP alongside your biological age. Upload your blood tests, see your PhenoAge instantly, and get personalized insights into which biomarkers need your attention most.
References
- Levine ME et al., “An epigenetic biomarker of aging for lifespan and healthspan,” Aging, 2018 — Original PhenoAge algorithm development
- Li Y et al., “Associations Between High-Sensitivity C-Reactive Protein and All-Cause Mortality Among Oldest-Old in Chinese Longevity Areas,” Frontiers in Public Health, 2022 — hs-CRP and mortality in long-lived populations
- Ferrucci L, Fabbri E, “Inflammageing: chronic inflammation in ageing, cardiovascular disease, and frailty,” Nature Reviews Cardiology, 2018 — Inflammaging as a central aging mechanism
- Ridker PM, “A Test in Context: High-Sensitivity C-Reactive Protein,” Journal of the American College of Cardiology, 2016 — Clinical utility and risk stratification
- Calder PC et al., “Marine omega-3 fatty acids and inflammatory processes,” Nutrients, 2017 — EPA/DHA and CRP reduction
- Pearson TA et al., “Markers of Inflammation and Cardiovascular Disease,” Circulation, 2003 — AHA/CDC guidelines for hs-CRP interpretation
- Ma LZ et al., “Plasma proteomics identify novel biomarkers and dynamic patterns of biological aging,” Journal of Advanced Research, 2025 — UK Biobank proteomics and aging pathways
- Li J et al., “Dynamic changes in hs-CRP and risk of all-cause mortality among middle-aged and elderly adults: findings from a nationwide prospective cohort and mendelian randomization,” Aging Clinical and Experimental Research, 2024 — Longitudinal hs-CRP tracking and mortality
- “TYPE Original Research: hs-CRP/HDL-C ratio and sarcopenia risk,” Frontiers in Immunology, 2025 — hs-CRP/HDL-C ratio as sarcopenia predictor
- Zhang et al., “hs-CRP/HDL-C can predict the risk of all cause mortality in cardiovascular-kidney-metabolic syndrome stage 1-4 patients,” Frontiers in Endocrinology, 2025 — hs-CRP/HDL-C ratio in CKM syndrome mortality prediction
- “A Conceptual Digital Health Framework for Longevity Optimization: Inflammation-Centered Approach Integrating Microbiome and Lifestyle Data,” Nutrients, January 2026 — Longevity-Inflammation Index (L-II) proposal
- Xie et al. (2025), “Colchicine and cardiovascular events: An updated meta-analysis of published randomized controlled trials,” Journal of Internal Medicine — Anti-inflammatory pharmacotherapy and CV events
- Navarese EP et al., “Causal effects of inflammation on long-term mortality: A Mendelian randomization study,” Aging, 2026 — IL-6 pathway causal signals and CRP as downstream marker
- American College of Cardiology, “hsCRP: A Promising Risk Assessment Tool,” 2025 — hs-CRP ≥2 mg/L as a risk-enhancing factor and residual inflammatory risk marker
- Margara-Escudero HJ et al., “Mediterranean Diet Reduces Inflammation in Adults: A Systematic Review and Meta-Analysis of Randomized Controlled Trials,” Nutrition Reviews, 2025 — Mediterranean diet effects on hs-CRP and inflammatory biomarkers
- “Dose-dependent effects of omega-3 polyunsaturated fatty acids on cardiometabolic markers,” 2025 — EPA/DHA dose-response effects on CRP in cardiometabolic disorders
Last updated: 2026-06-26. This article is regularly reviewed to ensure accuracy.
Related Articles
hs-CRP normal range: when does low-grade inflammation actually matter?
hs-CRP normal range explained: the low/medium/high cardiovascular risk thresholds, why under 1.0 mg/L is the longevity target, and how to read your number in context.

