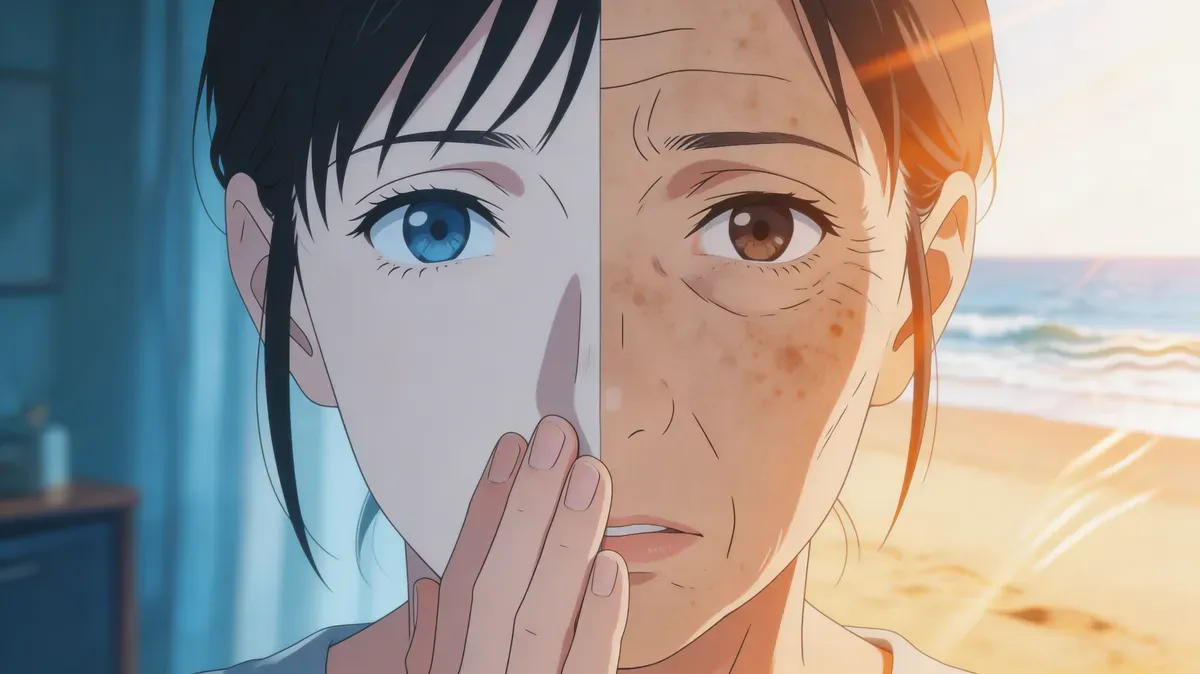
UV damage and photoaging: What the sun does to your biology beyond your skin
UV radiation causes far more than cosmetic aging. UVA degrades collagen via MMPs, UVB creates DNA mutations, and systemic inflammation follows. Here is the full science — and how to protect yourself.
Most people think of sun damage as a cosmetic problem — wrinkles, sunspots, leathery skin. But the story the science is telling is far more consequential. Ultraviolet radiation does not merely accelerate the surface appearance of aging; it drives biological aging at the cellular and molecular level in ways that intersect with virtually every major hallmark of aging — from DNA damage accumulation to chronic inflammation to collagen matrix collapse.
A 2013 study published in Clinical, Cosmetic and Investigational Dermatology estimated that solar UV radiation is responsible for approximately 80% of visible facial aging. But beneath that visible surface, UV is driving processes that affect skin barrier integrity, systemic inflammatory load, immune surveillance, and even epigenetic clocks. The sun is not merely aging your face — it is, through a chain of biological consequences, contributing to the aging of your entire body.
What you’ll learn:
- The molecular distinction between UVA and UVB damage — and why it matters
- How UV radiation degrades collagen, accelerates DNA mutation accumulation, and promotes systemic inflammation
- The photoaging-vitamin D paradox and how to navigate it
- Eight photoprotection strategies grounded in longevity science
What is photoaging and how is it different from intrinsic aging?
Photoaging refers specifically to the premature aging of the skin and underlying tissues caused by chronic ultraviolet radiation exposure, as distinct from intrinsic (chronological) aging, which occurs independently of environmental exposures.
Quick definition: Photoaging is the accelerated deterioration of skin structure, DNA integrity, and immune function driven by cumulative UV radiation exposure — distinct from, and additive to, normal chronological aging.
The distinction matters enormously in biological age research. Intrinsic aging produces a gradual, relatively uniform decline in collagen production (approximately 1% per year after age 20), epidermal cell turnover, and elastin integrity. Photoaging superimposes a much more aggressive degradation pattern on top of this baseline — producing wrinkle depths, collagen fragmentation, and inflammatory profiles that mirror intrinsically aged skin decades younger.
Sun-protected areas of the body — the inner arm, the lower back, the buttocks — typically look and function biologically much younger than chronologically equivalent sun-exposed areas. This difference is measurable not just cosmetically but in tissue collagen density, DNA mutation burden, and inflammatory marker expression.
The science: UVA, UVB, and what each does to your biology
UV radiation is divided into three bands. UVC (100-280 nm) is absorbed entirely by the ozone layer and does not reach the Earth’s surface under normal conditions. UVA (315-400 nm) and UVB (280-315 nm) both reach skin with different penetration depths and mechanisms of damage.
UVA: the deep penetrator
UVA constitutes approximately 95% of UV radiation reaching Earth’s surface. It penetrates through glass (car windows, office windows), through clouds, and reaches the dermis — the deep collagen-rich layer of skin beneath the epidermis. This penetration depth is the key to understanding UVA’s role in aging.
Collagen destruction via matrix metalloproteinases (MMPs)
UVA activates a cascade of signaling molecules inside skin cells that dramatically upregulates matrix metalloproteinases — enzymes that degrade structural proteins including collagen types I and III. MMPs are normally part of controlled tissue remodeling processes. Under UVA stimulation, they become overexpressed and begin degrading collagen faster than it can be synthesized. A single acute UVA exposure can increase collagen-degrading MMP-1 expression by up to 60-fold in dermal fibroblasts.
Repeated over years, this produces the dermal matrix degradation pattern characteristic of photoaged skin: loss of structural density, replacement of organized collagen fibers with fragmented and disorganized cross-linked collagen, and the visible collapse of skin architecture into wrinkles and laxity. The connection to glycation is direct: UVA-generated reactive oxygen species cross-link collagen in a process mechanistically similar to dietary AGE (advanced glycation end product) formation — making UV damage and dietary sugar two converging pathways toward the same structural deterioration.
Indirect DNA damage via reactive oxygen species
Unlike UVB, UVA does not directly absorb into DNA with high efficiency. Instead, it generates reactive oxygen species (ROS) that attack DNA indirectly, primarily creating 8-oxo-7,8-dihydroguanine (8-OHdG) lesions — one of the most mutagenic forms of oxidative DNA damage. Mitochondrial DNA, which is particularly susceptible to oxidative attack, accumulates 8-OHdG lesions from UVA at significantly higher rates than nuclear DNA.
UVB: the direct DNA mutagen
UVB, though comprising only 5% of surface UV radiation, is directly absorbed by DNA and produces characteristic cyclobutane pyrimidine dimers (CPDs) and 6-4 photoproducts — specific structural distortions in the DNA double helix at thymine-thymine and cytosine-thymine junctions. These mutations produce the distinctive CC→TT signature that is the molecular fingerprint of UV mutagenesis and drives the majority of squamous cell carcinomas and melanomas.
The skin has nucleotide excision repair (NER) machinery that removes these lesions, but repair efficiency declines with age — making cumulative UVB exposure increasingly mutagenic as you get older. In photoaged skin, UVB-signature mutations accumulate in stem cell populations that produce new keratinocytes, propagating mutation burden across successive generations of cells.
The Fitzpatrick scale and UV vulnerability
Skin types I-II (very fair, burns easily) generate significantly more UVB-induced CPDs per unit of UV exposure than types V-VI (deep brown or black, rarely burns). Melanin acts as a broad-spectrum UV filter, but it does not completely block UVA damage in any skin type — making photoprotection relevant for everyone across the Fitzpatrick spectrum.
The systemic inflammation pathway
This is the mechanism that elevates photoaging from a local skin problem to a systemic biological concern. UV-damaged keratinocytes and dermal cells release interleukin-1 beta (IL-1β), IL-6, TNF-alpha, and prostaglandins into the dermal microcirculation. In acutely sunburned skin, this local inflammation is obvious — heat, redness, swelling.
What is less obvious is that chronic subclinical UV exposure without visible burning still elevates these systemic inflammatory mediators, contributing to the background state of inflammaging. In people with extensive chronic sun exposure, skin barrier impairment — driven by UV degradation of tight junction proteins and epidermal lipids — allows bacterial antigens and allergens to penetrate the dermis, further amplifying systemic inflammatory load. This connects photoaging mechanistically to the broader inflammaging picture that underlies accelerated biological aging.
UV radiation and immunosuppression
Repeated UV exposure causes cumulative immunosuppression through depletion and dysfunction of epidermal Langerhans cells — the skin’s resident immune surveillance cells — and through UV-driven induction of regulatory T cells that suppress anti-tumor immunity. This systemic immunosuppression is considered one mechanism by which chronic UV exposure promotes both skin cancers and potentially facilitates other age-related immune dysfunction.
The vitamin D paradox: sun exposure’s double-edged relationship with longevity
UV radiation — specifically UVB in the 295-315 nm range — is the primary driver of endogenous vitamin D synthesis in the skin. UVB converts 7-dehydrocholesterol in the epidermis to pre-vitamin D3, which is then thermally isomerized and hydroxylated in the liver and kidneys to the active form, 1,25-dihydroxyvitamin D3.
Vitamin D is one of the most important longevity-relevant micronutrients — with receptors in virtually every tissue and critical roles in immune regulation, bone metabolism, cardiovascular function, and cancer suppression. Deficiency (below 20 ng/mL or 50 nmol/L) is strongly associated with accelerated biological aging, increased all-cause mortality, and higher risk of cancer, cardiovascular disease, and dementia.
The paradox is that the same UV exposure that damages collagen and DNA is also the most efficient source of vitamin D for most people. Supplement and dietary sources can compensate — and for most modern adults with limited intentional midday sun exposure, supplementation is likely necessary — but the paradox shapes how we think about sun exposure in a nuanced longevity framework.
Resolving the paradox in practice:
- Short, targeted UVB exposures during midday (10 AM to 2 PM), when the UVB:UVA ratio is highest, maximize vitamin D synthesis with minimal cumulative UVA burden
- Face, hands, and arms (approximately 25% of body surface area) exposed for 10-15 minutes (3-5 minutes for fair skin types) 3-4 times per week provides meaningful vitamin D synthesis
- Sunscreen applied to the face while leaving arms and legs briefly unprotected captures most of the photoprotection benefit while preserving some synthesis
- Regular blood testing (target: 40-60 ng/mL or 100-150 nmol/L) removes guesswork about whether your balance is working
8 photoprotection strategies for longevity
1. Use broad-spectrum SPF 30+ sunscreen daily, year-round
Consistent daily sunscreen application on chronically exposed areas — face, neck, hands, décolletage — is the single most evidence-supported intervention for reducing cumulative UV damage and its downstream biological consequences.
How to do it:
- Apply 0.07 oz (2 mL) to the face — most people apply 20-50% of the effective amount
- Reapply every 2 hours during prolonged outdoor exposure; SPF degrades with UV exposure and sweat
- Mineral sunscreens (zinc oxide, titanium dioxide) provide immediate broad-spectrum protection; chemical sunscreens require 20-30 minutes to activate
- SPF 30 blocks approximately 97% of UVB; SPF 50 blocks 98%; the difference beyond SPF 50 is minimal — consistency matters far more than number
2. Prioritize UVA protection, not just SPF
SPF ratings measure UVB protection only. UVA — the primary driver of collagen degradation and deep dermis aging — is rated separately, and many sunscreens provide inadequate UVA coverage despite high SPF numbers.
How to check UVA protection:
- In the US, look for “broad spectrum” designation on the label
- In Europe, look for the UVA circle logo (indicates UVA protection is at least one-third of the SPF)
- Zinc oxide provides the broadest UVA coverage of all sunscreen actives, particularly above 370 nm
3. Wear UV-protective clothing and hats during extended outdoor time
Physical UV barriers outperform sunscreen in two ways: they do not require reapplication and they eliminate the human error of insufficient or uneven application. UPF 50+ clothing blocks 98% of UV radiation through the fabric.
Practical choices:
- Wide-brim hats (minimum 3-inch or 7.6 cm brim) protect the face, neck, and ears
- Long-sleeved UPF shirts for hiking, gardening, and extended outdoor work
- UV-blocking window film for car side windows (front windshields have UV lamination; side windows typically do not)
4. Time outdoor activities to minimize peak UV exposure
UV intensity varies significantly throughout the day and year. The UV index is highest between 10 AM and 4 PM, peaking around solar noon. Exercising outdoors before 9 AM or after 5 PM during summer dramatically reduces cumulative UV dose.
Practical timing:
- Pre-dawn or early morning runs in summer: UV index typically below 2 (low risk)
- Midday outdoor work requires maximum photoprotection effort
- Shadow rule: if your shadow is shorter than your height, UV intensity is high and protection is critical
5. Protect your hands and neck consistently
The hands and neck are often neglected despite being among the most chronically exposed body surfaces. They are also among the most visible indicators of biological age — and the most sensitive to UV-driven collagen degradation due to thinner, more fragile skin.
How to do it:
- Include the hands and neck in your daily sunscreen routine
- UV-blocking driving gloves significantly reduce hand exposure during daily commuting
- Apply sunscreen to the back of hands after each handwashing and reapplication
6. Incorporate antioxidant support for UV-induced oxidative damage
Topical and dietary antioxidants do not replace sunscreen but provide meaningful complementary protection against UV-induced ROS and inflammatory signaling.
Evidence-based options:
- Topical vitamin C (L-ascorbic acid): Neutralizes UV-generated free radicals and supports collagen synthesis. Apply a stabilized vitamin C serum in the morning under sunscreen
- Dietary carotenoids: Lycopene (tomatoes, watermelon), beta-carotene (carrots, sweet potatoes), and lutein (leafy greens) accumulate in skin tissue and provide modest but measurable photoprotection — equivalent to approximately SPF 2-4 when tissue levels are high. Lutein also concentrates in the macula, where UV exposure is a key driver of age-related macular degeneration. Astaxanthin, a carotenoid found in wild salmon and krill, is particularly notable: it crosses the blood-retinal barrier, spans the full width of cell membranes, and can increase the minimum erythema dose in clinical trials — functioning as an internal amplifier of UV defense in both skin and retinal tissue
- Omega-3 fatty acids: Reduce UV-induced prostaglandin E2 production and suppress MMP activity
- Polyphenols: Green tea catechins and resveratrol modulate NF-κB — a master regulator of UV-induced inflammatory signaling
7. Address UV-related collagen loss through targeted nutrition
Collagen synthesis requires specific nutritional substrates. Supporting this pathway both counteracts photoaging-driven degradation and contributes to systemic connective tissue health.
Key nutrients:
- Vitamin C: Essential cofactor for prolyl hydroxylase, the enzyme that synthesizes collagen’s hydroxyproline backbone. Deficiency severely impairs collagen production regardless of other factors
- Glycine, proline, and hydroxyproline: The primary amino acids of collagen. Found in bone broth, skin-on fish, and gelatin
- Zinc: Required for MMP regulation; adequate zinc levels help limit excessive MMP activity driven by UV exposure
- Silica: Found in oats, leeks, and cucumber; contributes to glycosaminoglycan synthesis in the dermis
8. Treat cumulative UV damage as an epigenetic clock input
Photoaging is not purely cosmetic — it is a legitimate biological age input. Research using the SkinAge epigenetic clock, specifically trained on UV exposure history, found that photoaged skin showed biological ages 10-20 years ahead of intrinsically aged skin controls. Treating UV damage with the same seriousness as cardiovascular risk or metabolic biomarkers is scientifically justified.
Practical implication: Annual skin checks by a dermatologist serve as biological audits. Actinic keratoses, solar lentigines, and dermatoheliosis are not merely cosmetic — they are visible evidence of accumulated DNA mutation burden and collagen matrix degradation, signaling broader biological aging that is likely occurring in less visible tissues through the same systemic mechanisms.
Tracking photoaging and its biological consequences
Visible and measurable photoaging markers
| Marker | What it signals | Assessment method |
|---|---|---|
| Fitzpatrick wrinkling scale | Cumulative UV damage to dermis | Clinical or self-assessment |
| Actinic keratoses (count) | UVB mutation burden in skin | Dermatologist exam |
| Solar lentigines | Melanocyte UV damage | Visual assessment |
| Skin elasticity | Collagen/elastin integrity | Clinical tonometer or handheld device |
| hs-CRP | Systemic inflammatory load from UV | Blood test |
Blood biomarkers to monitor
- 25-hydroxyvitamin D: Reflects the UV-synthesis/supplementation balance; target 40-60 ng/mL (100-150 nmol/L)
- hs-CRP: Chronic UV exposure contributes to systemic inflammation detectable in serum
- MMP-1 and MMP-3: Available in research panels; elevated in chronically photoaged individuals
How SuperAge connects photoaging to your biological age
Photoaging is one of the environmental inputs that connects UV exposure history to systemic biological aging — through the shared mechanisms of collagen degradation, chronic inflammation, DNA damage accumulation, and immune dysfunction. These same mechanisms are reflected in the physiological metrics that SuperAge tracks daily.
Chronic UV-driven inflammation elevates resting heart rate, suppresses heart rate variability, and disrupts sleep architecture — all metrics that SuperAge monitors through Apple Watch and HealthKit. As you improve your photoprotection habits and reduce systemic inflammatory load, these metrics respond measurably over weeks and months.
The connection runs deeper: vitamin D optimization — achieved through a calibrated balance of intentional sun exposure and supplementation — has documented effects on cardiovascular function, immune regulation, and sleep quality, all of which feed directly into SuperAge’s biological age calculation. Understanding that sunscreen use, vitamin D status, and UV timing choices have real biological consequences beyond cosmetics is a perspective shift that makes consistent photoprotection easier to sustain.
Download SuperAge to monitor the biomarkers most sensitive to UV-driven systemic aging and track the impact of your photoprotection strategies in real time.
Frequently asked questions
Does sunscreen prevent vitamin D synthesis?
Yes — SPF 30 reduces cutaneous vitamin D synthesis by approximately 95% when applied at the correct dose (2 mg/cm²). However, most people apply less than half the effective amount, and people rarely cover their entire body surface area. In practice, realistic sunscreen use reduces but does not eliminate vitamin D synthesis. Monitoring serum vitamin D and supplementing as needed is the recommended approach rather than avoiding sunscreen.
Is photoaging reversible?
Partially. Retinoids (topical tretinoin and retinol) are the most evidence-supported topical interventions, increasing collagen synthesis, normalizing abnormal keratinocyte differentiation, and partially reversing epidermal thinning from UV exposure. Laser resurfacing, radiofrequency devices, and chemical peels can improve collagen architecture. Epigenetically, removing UV exposure and reducing inflammatory burden allows some methylation clock reversal, though extensively photoaged skin will not fully return to baseline.
How does UV damage compare to smoking in terms of biological aging?
Both involve overlapping mechanisms — oxidative stress, collagen degradation, DNA damage, inflammation — but in different tissue distributions. Smoking produces more systemic cardiovascular and pulmonary aging; UV produces more focal dermal and immune aging. Combined exposure is particularly damaging, as smoking compromises antioxidant defenses that would otherwise partially buffer UV-induced ROS.
Does cloud cover protect against UV damage?
Partially. Light overcast reduces UV by approximately 20-40%; heavy overcast by 50-90%. However, UV reflectance from surfaces (water: 25%, snow: 80%, sand: 15%) compensates substantially. Up to 80% of UV radiation penetrates light cloud cover — enough to drive photoaging over years of cumulative exposure.
How much daily sun exposure is safe for vitamin D without significant UV aging?
For most adults at temperate latitudes (35-55°N), 10-15 minutes (3-8 minutes for Fitzpatrick type I-II skin) of midday sun exposure on approximately 25% of body surface area (arms and hands) 3-4 times per week provides meaningful vitamin D synthesis with a modest cumulative UV burden. Protecting the face with sunscreen during this time is recommended given the face’s high sensitivity to UV aging and its disproportionate contribution to perceived biological age.
Key takeaways
- UV damage goes far beyond cosmetics: UVA drives collagen destruction via MMPs, UVB causes direct DNA mutations, and both contribute to systemic inflammation and immune dysfunction
- UVA is the primary anti-aging concern: It penetrates through glass, clouds, and clothing, and drives the majority of collagen degradation and deep dermis aging
- Systemic consequences are real: UV-driven skin barrier impairment and inflammatory signaling contribute to whole-body inflammaging, not just local skin damage
- The vitamin D paradox requires calibration: Short, intentional midday UVB exposures for synthesis, combined with daily sun protection for chronically exposed areas, resolve the apparent conflict between protection and sufficiency
- Consistent broad-spectrum SPF 30+ is the single highest-impact intervention: Applied daily to exposed areas, it reduces cumulative UV-driven biological aging more than any other photoprotection tool
Protect your biology, not just your complexion
UV radiation is one of the few quantified external causes of accelerated biological aging — and one of the most preventable. Every application of sunscreen is not merely a cosmetic choice; it is a concrete action to reduce DNA mutation accumulation, collagen degradation, and systemic inflammatory load.
Ready to track how your lifestyle choices affect your biological age? Download SuperAge and see the biomarkers that connect UV exposure, vitamin D status, and inflammation to your true biological age.
References
- Flament F et al. (2013). “Effect of the sun on visible clinical signs of aging in Caucasian skin.” Clinical, Cosmetic and Investigational Dermatology, 6, 221–232.
- Fisher GJ et al. (1996). “Molecular basis of sun-induced premature skin ageing and retinoid antagonism.” Nature, 379(6563), 335–339.
- Brenner M & Hearing VJ (2008). “The protective role of melanin against UV damage in human skin.” Photochemistry and Photobiology, 84(3), 539–549.
- Yaar M & Gilchrest BA (2007). “Photoageing: mechanism, prevention and therapy.” British Journal of Dermatology, 157(5), 874–887.
- Schuch AP et al. (2017). “UV damage and DNA repair in the skin.” Genetics and Molecular Biology, 40(suppl 1), 314–324.
- Gruber F et al. (2020). “The connected consequences of photoaging and photoprotection.” Photodermatology, Photoimmunology & Photomedicine, 36(2), 89–95.
- Holick MF (2004). “Sunlight and vitamin D for bone health and prevention of autoimmune diseases, cancers, and cardiovascular disease.” The American Journal of Clinical Nutrition, 80(6), 1678S–1688S.
- Pandel R et al. (2013). “Skin photoaging and the role of antioxidants in its prevention.” ISRN Dermatology, 2013, 930649.
Last updated: 2026-03-19. This article is reviewed regularly to ensure accuracy.
The information provided does not replace professional medical advice. Consult your doctor before making significant changes to your lifestyle.
Related Articles

Astaxanthin: super-carotenoid for skin, eyes and aging
Astaxanthin may support skin UV resilience, eye fatigue, and oxidative-stress markers. Review doses, safety limits, food sources, and realistic aging claims.

