Leptin resistance vs insulin resistance: how they differ
Leptin resistance vs insulin resistance compares appetite signaling with glucose handling. Learn how they differ, overlap, and what labs or patterns to track.
Leptin resistance and insulin resistance sound like the same metabolic problem with two different hormone names. They are not.
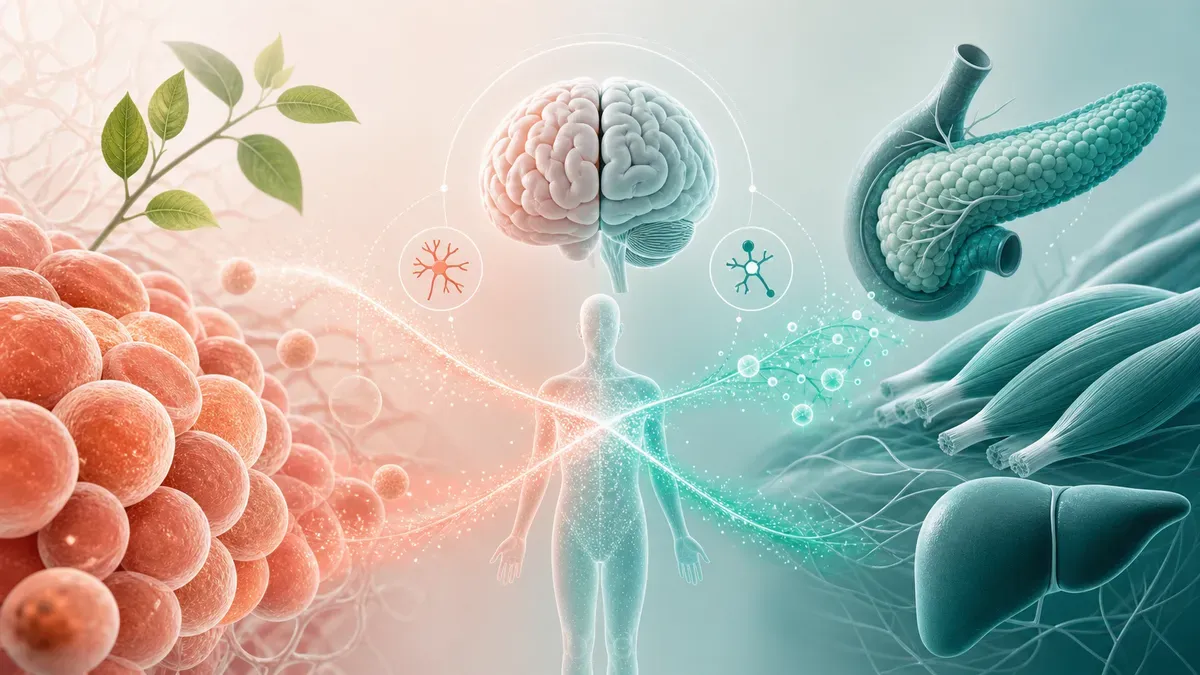
Leptin is mostly a fat-to-brain signal. It tells the brain how much stored energy is available and helps regulate hunger, satiety, energy expenditure, reproductive function, thyroid tone, and the body’s response to weight loss.
Insulin is mostly a pancreas-to-tissue signal. It helps move glucose into muscle, liver, and fat cells, suppresses liver glucose output, and coordinates fuel storage after meals.
When people say leptin resistance, they usually mean the brain is not responding appropriately to a high leptin signal from fat tissue. The practical pattern is often persistent hunger, weak satiety, strong food drive, weight regain pressure after weight loss, and higher body fat despite high circulating leptin. When people say insulin resistance, they mean muscle, liver, fat, or other tissues need more insulin than usual to handle glucose and fuel traffic.
They overlap because both travel through adipose tissue, inflammation, sleep, stress, muscle, and body composition. But they answer different questions:
- Leptin resistance asks: why does the body still behave as if stored energy is not enough?
- Insulin resistance asks: how much insulin is required to keep glucose and fuel metabolism under control?
For the complete insulin-sensitivity guide, start with how to improve insulin sensitivity. This article focuses on the comparison: appetite and satiety signaling versus glucose and insulin signaling.
What you’ll learn:
- How leptin resistance differs from insulin resistance
- Why high leptin does not automatically mean a useful diagnosis
- Which pattern is easier to measure
- How the two forms of resistance reinforce each other
- What labs, body-composition signals, and wearable trends to track
The short answer
Leptin resistance and insulin resistance are related, but they are not interchangeable.
| Feature | Leptin resistance | Insulin resistance |
|---|---|---|
| Main hormone source | Fat cells | Pancreatic beta cells |
| Main target | Brain appetite and energy-balance circuits, plus peripheral tissues | Muscle, liver, fat, and other insulin-sensitive tissues |
| Core signal | “Stored energy is available” | “Move and store fuel after eating” |
| Common pattern | High body fat, high leptin, persistent hunger, weak satiety, weight-regain pressure | High fasting insulin, high HOMA-IR, post-meal spikes, high triglycerides, fatty-liver or waist pattern |
| Best measurement | Inferred from body fat, leptin context, hunger and regain pattern; fasting leptin is not enough alone | Fasting insulin, fasting glucose, HOMA-IR, TyG index, OGTT, CGM, lipids, waist |
| Practical first step | Make appetite signals easier to hear: sleep, protein, fiber, less ultra-processed food, sustainable fat loss | Reduce insulin demand: muscle, movement, sleep, lower glycemic load, visceral-fat reduction |
If you are trying to decide which one to act on first, insulin resistance is usually easier to verify because it has better routine markers: fasting insulin, HOMA-IR, glucose, HbA1c, triglycerides, HDL-C, waist, and blood pressure.
Leptin resistance is real biology, but it is harder to diagnose in everyday practice. A high leptin level often reflects higher fat mass. A low leptin level can reflect low fat mass, prolonged calorie restriction, or recent weight loss. Neither result alone proves whether your brain is listening to leptin.
The most useful approach is to track both sides:
- Use labs to estimate insulin resistance.
- Use appetite, satiety, weight-regain pressure, sleep, body composition, and food environment to infer leptin-related pressure.
- Treat the shared drivers: visceral fat, poor sleep, low muscle, ultra-processed food, inactivity, stress, and inflammation.
What leptin does
Leptin is a hormone made mostly by adipocytes, or fat cells. In general, more fat mass means more leptin in the blood. That was one of the major findings in the early human leptin studies: serum leptin rose strongly with body fat percentage.
The basic signal is simple:
- Higher leptin usually tells the brain that energy stores are sufficient.
- Lower leptin tells the brain that stored energy is low or falling.
But leptin is not a simple “stop eating” switch. It is more like an energy-availability signal. When leptin falls, the brain can respond by increasing hunger, reducing energy expenditure, altering thyroid and reproductive signaling, and making weight maintenance feel harder. This is why leptin matters during weight loss: after fat loss, leptin drops more than many people expect, and the body can interpret the reduced state as a relative energy shortage.
Rare congenital leptin deficiency is a different situation. In those cases, leptin replacement can be transformative under specialist care. That does not mean leptin supplementation is a general obesity treatment. In common obesity, leptin is often already high. The issue is usually not “no leptin”; it is that the system is not responding to the signal in the expected way.
For body-composition context, see visceral fat normal but waist high and how to reduce visceral fat.
What insulin does
Insulin is released by the pancreas when glucose and other nutrient signals rise. Its job is to coordinate fuel handling.
At a high level, insulin:
- helps muscle and fat cells take up glucose
- suppresses liver glucose output
- supports glycogen storage
- helps regulate fat storage and fat release
- signals that nutrients are available
Insulin resistance means cells do not respond as efficiently. The pancreas compensates by making more insulin. For a while, glucose can look normal because the extra insulin is doing the work. That is why a person can have normal fasting glucose but high fasting insulin.
The standard early pattern is:
- Muscle, liver, or fat cells become less insulin-sensitive.
- The pancreas secretes more insulin.
- Fasting glucose and HbA1c may stay normal.
- Fasting insulin, HOMA-IR, triglycerides, waist, or post-meal glucose may reveal the strain earlier.
For that exact lab pattern, read fasting glucose normal but insulin high. For marker sequencing, use fasting insulin vs HbA1c vs glucose.
The core difference: appetite signal vs glucose signal
The cleanest distinction is this:
Leptin resistance is mostly about energy-store sensing.
Your fat tissue may be sending a strong “energy is available” signal, but the brain’s response does not match. The result can be hunger, low satiety, lower spontaneous activity, weight-regain pressure, and a stronger drive toward calorie-dense foods.
Insulin resistance is mostly about fuel handling.
Your pancreas may be sending a strong “move glucose and manage fuel” signal, but tissues do not respond efficiently. The result can be high insulin, high HOMA-IR, post-meal glucose spikes, fatty-liver physiology, high triglycerides, and eventually rising glucose or HbA1c.
They can coexist, but one does not prove the other.
Example 1: high leptin, modest insulin resistance
A person with high body fat may have high leptin because leptin tracks fat mass. If fasting insulin, HOMA-IR, triglycerides, glucose, blood pressure, and waist trend are still favorable, the insulin-resistance side may be modest. The appetite/weight-regulation side may still be difficult, but the glucose system is not necessarily failing.
Example 2: strong insulin resistance, unclear leptin pattern
A person with normal BMI but low muscle, high waist-to-height ratio, high triglycerides, and high fasting insulin may be insulin-resistant even without obvious high body fat. Leptin may not be the main signal to chase. This is why insulin resistance can exist in lean people and why body weight alone is a poor screen.
Example 3: post-weight-loss hunger with lower leptin
After weight loss, leptin often drops with fat mass and calorie restriction. Hunger can rise, energy expenditure can fall, and the body may defend the previous weight. That is not the same as classic high-leptin resistance. It may be a relative low-leptin state after weight reduction.
This distinction matters because “fix leptin resistance” advice often collapses all three cases into one oversimplified story.
Why they overlap
Leptin and insulin resistance often appear together because they share upstream drivers.
| Shared driver | Effect on leptin side | Effect on insulin side |
|---|---|---|
| Visceral fat | Higher leptin load, inflammatory signaling, disrupted appetite regulation | Inflammation, fatty-liver physiology, higher fasting insulin |
| Poor sleep | Lower satiety control, higher hunger and cravings | Reduced insulin sensitivity, higher next-day glucose response |
| Ultra-processed food | Weak satiety per calorie, reward-driven intake | Higher glycemic load, energy surplus, liver fat risk |
| Low muscle mass | Lower energy expenditure and lower glucose sink | Higher insulin demand for the same meal |
| Chronic stress | Higher food drive, emotional eating, sleep disruption | Cortisol-driven glucose output and insulin resistance |
| Weight cycling | Leptin drops during weight loss, regain pressure rises | Regain often restores visceral fat and worsens metabolic markers |
This is why the same lifestyle changes can improve both patterns without needing to know which hormone “started it.”
Better sleep can improve appetite regulation and insulin sensitivity. Resistance training can improve glucose disposal and body-composition trajectory. Protein and fiber can improve satiety and reduce post-meal insulin demand. Reducing visceral fat can lower inflammatory pressure on both systems.
For the sleep-metabolic link, see sleep regularity vs sleep duration and morning glucose spike vs post-meal spike.
Can you test leptin resistance?
You can measure fasting leptin, but the result is not as clinically straightforward as fasting insulin.
A leptin test can tell you whether circulating leptin is low, typical, or high for the assay. It does not prove whether hypothalamic leptin signaling is working. High leptin often means higher fat mass. Low leptin often means low fat mass, recent weight loss, prolonged calorie restriction, under-fueling, or rare leptin deficiency.
In research, leptin interpretation is often adjusted for fat mass, sex, age, and energy balance. In everyday labs, most people do not get that level of interpretation.
Practical leptin-related clues include:
- strong hunger despite adequate protein, fiber, and calories
- poor satiety after meals that should be filling
- strong weight-regain pressure after fat loss
- low spontaneous activity or cold intolerance after aggressive dieting
- high body fat with high hunger and low satiety
- short sleep paired with stronger cravings
Those clues are not diagnostic. They are pattern signals. They should make you look at sleep, energy availability, food environment, dieting history, body composition, and metabolic labs together.
How to test insulin resistance
Insulin resistance is easier to estimate because several markers are practical.
| Marker | What it tells you |
|---|---|
| Fasting insulin | How much insulin is needed at rest |
| Fasting glucose | Whether fasting glucose is still controlled |
| HOMA-IR | Fasting insulin and glucose combined |
| HbA1c | Average glucose exposure over about 2 to 3 months |
| Triglycerides and HDL-C | Lipid pattern often linked with insulin resistance |
| TyG index | Insulin-resistance surrogate from triglycerides and glucose |
| CGM or OGTT | Meal response and glucose tolerance |
| Waist-to-height ratio | Central adiposity signal |
No single marker is perfect. Fasting insulin varies by lab and context. HOMA-IR is an estimate, not a clamp test. CGM can miss early compensated insulin resistance if insulin is still holding glucose in range. But together, these markers are much more actionable than guessing from appetite alone.
For a practical formula guide, use HOMA-IR explained. For glucose patterns, use CGM for non-diabetics.
Which should you prioritize?
Prioritize the pattern you can verify and act on.
Prioritize insulin resistance when labs are moving
If fasting insulin, HOMA-IR, triglycerides, waist, blood pressure, ALT, GGT, glucose, or HbA1c are worsening, act on insulin resistance first. It is measurable, clinically relevant, and tightly linked to cardiometabolic risk.
The first moves are not exotic:
- resistance training
- walking after meals
- higher protein adequacy
- higher fiber
- lower refined carbohydrate load
- better sleep
- visceral-fat reduction if needed
- less alcohol if it worsens liver or sleep markers
Prioritize leptin-related pressure when hunger and regain dominate
If labs are fairly stable but hunger, cravings, regain pressure, and low satiety are the main problem, think in leptin-related terms.
The first moves are:
- stop aggressive crash dieting
- keep the calorie deficit modest if weight loss is needed
- maintain protein at each meal
- increase high-volume, high-fiber foods
- reduce ultra-processed, hyper-palatable foods at home
- protect sleep duration and regularity
- strength train to preserve lean mass during fat loss
- track weight trend, waist, and appetite together rather than only scale weight
In other words, do not try to “hack leptin” with a supplement. Make the environment and physiology easier for satiety signals to work.
Prioritize both when body composition and labs disagree
Many people sit in the overlap zone: higher waist, high hunger, rising fasting insulin, and poor sleep. In that case, do not choose one hormone. Use a combined metabolic-recovery plan.
For example:
- Repeat fasting glucose, fasting insulin, lipids, and HbA1c.
- Track waist and weight trend weekly.
- Add 2 to 3 resistance sessions per week.
- Walk after the largest meal.
- Build meals around protein, fiber, and minimally processed carbohydrates.
- Keep sleep timing consistent for 2 weeks before judging appetite.
- Recheck labs after 8 to 12 weeks.
How SuperAge helps connect the signals
Leptin resistance and insulin resistance are hard to understand from one datapoint. SuperAge helps because it tracks the surrounding pattern.
Use SuperAge to connect:
- sleep duration and hunger the next day
- HRV and cravings during stress weeks
- resting heart rate and metabolic strain
- activity regularity and waist trend
- strength training and body-composition change
- fasting insulin, glucose, HbA1c, triglycerides, and biological-age trend
- post-meal movement and glucose recovery if you also use CGM
This matters because appetite is not just willpower and glucose is not just carbohydrates. A week of short sleep can worsen both food drive and insulin sensitivity. A month of resistance training can improve glucose disposal before the scale changes much. A stable weight with shrinking waist and better HOMA-IR is a very different pattern from stable weight with rising waist and rising insulin.
SuperAge gives you the trend context that a single hormone test cannot.
What not to do
Avoid these common mistakes:
Do not diagnose leptin resistance from hunger alone
Hunger can come from under-eating, low protein, low fiber, poor sleep, stress, medications, menstrual-cycle phase, perimenopause, high training load, depression, or highly palatable food exposure. Leptin may be part of the story, but hunger alone is not proof.
Do not assume high leptin means leptin is the root cause
High leptin often reflects higher fat mass. The more useful question is whether the whole pattern suggests impaired appetite regulation, weight-regain pressure, inflammation, or cardiometabolic risk.
Do not ignore insulin because glucose is normal
Normal glucose does not rule out insulin resistance. If fasting insulin or HOMA-IR is high, the pancreas may be compensating. That is an early intervention window, not a reason to wait until glucose rises.
Do not use leptin therapy as a general weight-loss strategy
Leptin replacement has important specialist uses in rare leptin-deficiency or lipodystrophy contexts. Common obesity is usually not a simple leptin-deficiency state. Treating it as one can lead to expensive, ineffective, or unsafe decisions.
Frequently asked questions
Can you have leptin resistance without insulin resistance?
Possibly, but in everyday practice it is hard to prove. A person may have strong appetite and weight-regulation pressure without obvious glucose or insulin abnormalities. But because leptin resistance is not easy to diagnose from one lab, it is better to describe the pattern: hunger, satiety, body fat, sleep, dieting history, and weight-regain pressure.
Can you have insulin resistance without leptin resistance?
Yes. A person can have high fasting insulin, high HOMA-IR, fatty-liver risk, or high triglycerides without a clear appetite-regulation problem. Lean insulin resistance is a good example: the issue may be low muscle, visceral or ectopic fat, genetics, sleep apnea, medications, or liver metabolism rather than obvious high leptin.
Is leptin resistance why dieting feels harder after weight loss?
Leptin is part of it. Weight loss lowers leptin, and the body can respond with more hunger, lower energy expenditure, and stronger regain pressure. That is not always the same as high-leptin resistance. It can be a relative low-leptin signal after weight reduction.
Which lab should I order first?
For most people, start with insulin-resistance markers: fasting glucose, fasting insulin, HbA1c, triglycerides, HDL-C, and waist-to-height ratio. Add HOMA-IR from fasting glucose and insulin. Fasting leptin can be useful in selected cases, but it is not usually the first-line test for routine metabolic interpretation.
Do GLP-1 medications fix leptin resistance?
They do not simply “fix leptin resistance.” GLP-1 receptor agonists act through appetite, gastric emptying, glucose regulation, and brain reward pathways, and they can lead to major weight loss and improved insulin resistance in appropriate patients. Leptin biology may change as fat mass changes, but medication decisions belong with a clinician.
Key takeaways
- Leptin resistance is mostly an appetite and energy-store sensing problem. It is inferred from patterns, not diagnosed from hunger or one leptin value.
- Insulin resistance is mostly a glucose and fuel-handling problem. It is easier to estimate with fasting insulin, HOMA-IR, glucose, lipids, waist, OGTT, or CGM.
- High leptin often reflects high fat mass. It does not automatically prove that leptin is the primary root cause.
- Normal glucose does not rule out insulin resistance. High insulin can hide the strain for years.
- The overlap is where action matters. Sleep, muscle, visceral fat, protein, fiber, movement, and food environment influence both systems.
Track the signal, not just the hormone
Leptin and insulin are useful because they reveal systems, not because one lab number explains everything.
Ready to connect appetite, body composition, sleep, glucose, insulin, recovery, and biological age in one place? Download SuperAge and start tracking the patterns that show whether your metabolism is getting easier or harder to regulate.
References
- Friedman JM. “Leptin and the endocrine control of energy balance.” Nature Metabolism. 2019;1:754-764. doi:10.1038/s42255-019-0095-y.
- Considine RV, Sinha MK, Heiman ML, et al. “Serum immunoreactive-leptin concentrations in normal-weight and obese humans.” New England Journal of Medicine. 1996;334:292-295. doi:10.1056/NEJM199602013340503.
- Myers MG Jr, Leibel RL, Seeley RJ, Schwartz MW. “Obesity and leptin resistance: distinguishing cause from effect.” Trends in Endocrinology & Metabolism. 2010;21(11):643-651. doi:10.1016/j.tem.2010.08.002.
- Farooqi IS, O’Rahilly S. “20 years of leptin: human disorders of leptin action.” Journal of Endocrinology. 2014;223(1):T63-T70. doi:10.1530/JOE-14-0480.
- Reaven GM. “Role of insulin resistance in human disease.” Diabetes. 1988;37(12):1595-1607. doi:10.2337/diab.37.12.1595.
- Matthews DR, Hosker JP, Rudenski AS, Naylor BA, Treacher DF, Turner RC. “Homeostasis model assessment: insulin resistance and beta-cell function from fasting plasma glucose and insulin concentrations in man.” Diabetologia. 1985;28(7):412-419. doi:10.1007/BF00280883.
- Taheri S, Lin L, Austin D, Young T, Mignot E. “Short sleep duration is associated with reduced leptin, elevated ghrelin, and increased body mass index.” PLOS Medicine. 2004;1(3):e62. doi:10.1371/journal.pmed.0010062.
- Rosenbaum M, Sy M, Pavlovich K, Leibel RL, Hirsch J. “Low-dose leptin reverses skeletal muscle, autonomic, and neuroendocrine adaptations to maintenance of reduced weight.” Journal of Clinical Investigation. 2005;115(12):3579-3586. doi:10.1172/JCI25977.
Related Articles
How to reduce visceral fat: 6 strategies that actually work
Learn 6 evidence-based strategies to reduce visceral fat, the hidden belly fat linked to chronic disease. Includes exercise, diet, sleep, and tracking tips.