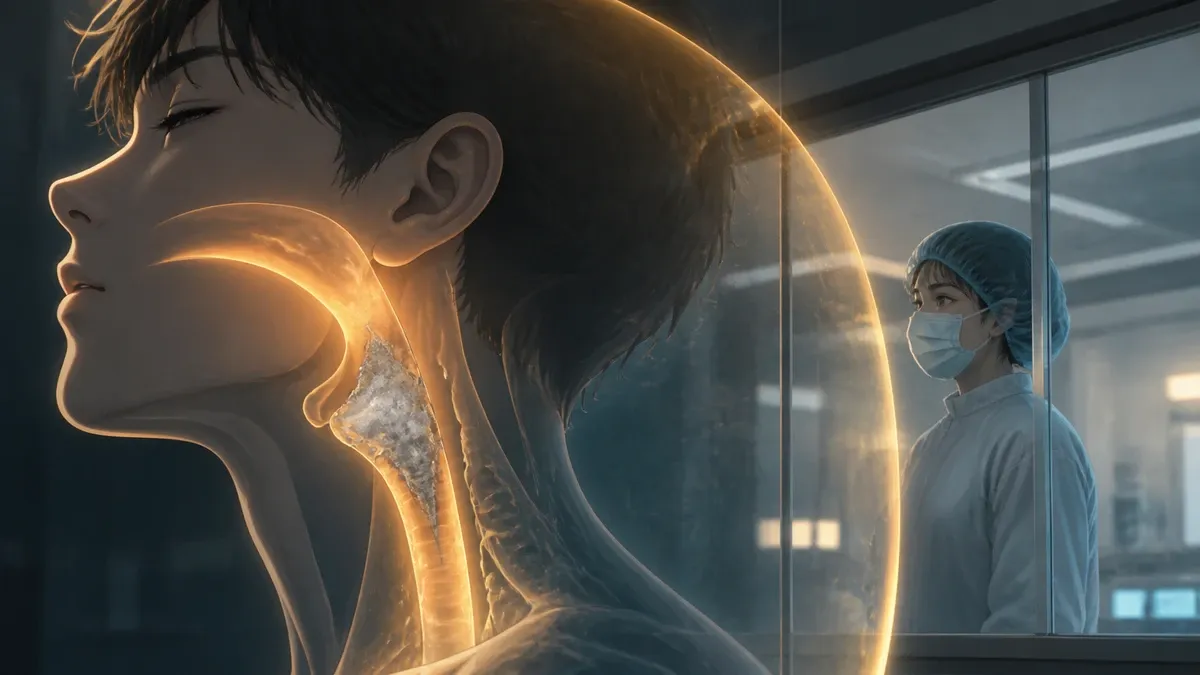
Diphtheria symptoms: gray membrane and emergency signs
Diphtheria symptoms can start with sore throat and a gray membrane. Learn emergency signs, diagnosis, treatment, contact steps, and prevention.
Diphtheria can begin gradually with a sore throat, weakness, swollen neck glands, trouble swallowing, and a low fever. Its classic warning sign is a tough gray or gray-white coating—called a pseudomembrane—over the tonsils, throat, or nose. The membrane can narrow the airway, while bacterial toxin can injure the heart, nerves, and kidneys.
Suspected respiratory diphtheria is an emergency even where the disease is uncommon. Do not scrape, swab, or try to remove a throat membrane yourself: it is firmly attached, forced removal can cause bleeding, and disturbing the airway is unsafe. Call local emergency or urgent medical services, describe the symptoms and possible exposure, and follow instructions that limit contact with other people. Treatment may need to begin before laboratory confirmation.
Quick answer
The symptom pattern that should raise concern is a gradually worsening sore throat plus an adherent gray membrane, neck swelling, difficulty swallowing, hoarseness, noisy breathing, or breathing difficulty—especially after close contact with a case, travel to an affected area, or incomplete vaccination.
A gray coating is not proof of diphtheria. Streptococcal throat infection, viral infections, infectious mononucleosis, candidiasis, and other conditions can resemble parts of the picture. But a person with breathing or swallowing difficulty, a firmly attached membrane, marked neck swelling, or systemic illness needs urgent professional assessment rather than a home throat test.
Key facts
- Toxigenic Corynebacterium bacteria can produce a toxin that destroys local tissue and forms an adherent pseudomembrane.
- The respiratory pseudomembrane can obstruct the nose, throat, or larynx and make breathing or swallowing difficult.
- Circulating diphtheria toxin can damage the heart muscle, peripheral nerves, and kidneys after the throat symptoms begin.
- Immediate presumptive treatment can reduce progression because antitoxin cannot undo toxin already fixed to tissue.
- Vaccination and booster doses can prevent toxin-mediated disease, but schedules and catch-up recommendations vary by country.
Emergency note: The World Health Organization advises prompt testing and treatment whenever diphtheria is suspected. Call local emergency services now for severe breathing difficulty, blue or gray lips, collapse, confusion, inability to swallow saliva, rapidly increasing neck swelling, or harsh/noisy breathing. Call ahead when possible so the care team can prepare infection-control precautions.
What diphtheria is—and why the gray membrane matters
Diphtheria is an infection caused by strains of Corynebacterium diphtheriae and, less commonly, other potentially toxin-producing Corynebacteria such as C. ulcerans. The bacteria can infect the respiratory tract or skin. The classic severe illness happens when a strain produces diphtheria toxin.
At the infection site, toxin blocks protein production inside cells. Injured tissue, inflammatory cells, bacteria, and fibrin bind together into a dense coating. Unlike loose mucus or ordinary tonsil exudate, the pseudomembrane is attached to the tissue below it. It may begin bluish-white and become gray, green-gray, or dark if bleeding occurs.
The visible membrane is only one part of the danger:
- Local danger: the coating and surrounding swelling can narrow the upper airway.
- Systemic danger: absorbed toxin can travel through the bloodstream and injure distant organs.
- Transmission danger: respiratory droplets and direct contact with infected secretions can spread the bacteria to close contacts.
The CDC clinical overview gives a usual incubation period of 2–5 days, with a range of 1–10 days. A person can also carry the bacteria without obvious symptoms. That is why exposure history and public-health follow-up matter even when someone feels well.
The symptom pattern clinicians look for
Respiratory diphtheria often starts less dramatically than people expect. High fever is not required; severe toxin effects can develop despite a low-grade temperature.
| Pattern | Why it matters | Safe response |
|---|---|---|
| Gradual sore throat, malaise, weakness, poor appetite, or low fever | Common early pattern, but nonspecific | Contact a clinician promptly if exposure or vaccination concerns exist |
| Tough gray-white coating on tonsils, throat, or nose | Classic pseudomembrane pattern | Do not touch it; arrange urgent assessment |
| Pain or difficulty swallowing, drooling, voice change, or hoarseness | May signal upper-airway involvement | Urgent same-day or emergency evaluation |
| Noisy breathing, stridor, pulling in at the ribs, or breathlessness | Possible airway narrowing | Call emergency services now |
| Swollen neck glands or extensive soft-tissue swelling (“bull neck”) | Can mark severe respiratory disease | Emergency evaluation |
| Palpitations, chest pain, faintness, new weakness, or trouble walking | Possible toxin-related cardiac or neurologic complication | Emergency or immediate clinical assessment |
| Slow-healing skin ulcer with a clear edge or gray membrane | Cutaneous infection is possible and can spread bacteria | Cover loosely, avoid direct contact, and seek prompt care |
The gray membrane is a warning sign, not a home diagnostic test
The CDC description of symptoms and complications identifies the pseudomembrane as the hallmark of respiratory disease. However, color alone is unreliable. A phone photo cannot show how firmly material is attached, whether the larynx is involved, or whether toxin is circulating.
Clinicians consider other explanations for a coated or inflamed throat, including group A streptococcal pharyngitis, infectious mononucleosis, viral pharyngitis, candidiasis, peritonsillar abscess, epiglottitis, trauma, and noninfectious lesions. Some of these also need urgent care. Do not use the absence of a perfect gray color to dismiss progressive swallowing or breathing symptoms.
Neck swelling can progress while fever stays modest
Enlarged cervical lymph nodes and swelling around the jaw and front of the neck can create the classic “bull neck” appearance. The person may look pale, weak, or acutely unwell. A rapid pulse can occur, but a wearable cannot identify diphtheria or rule out myocarditis. Our illness, resting-heart-rate, and HRV guide explains why physiologic trends provide context rather than a pathogen diagnosis.
Similarly, a normal watch oxygen value does not establish a safe airway. Consumer sensors can miss sudden obstruction and are affected by motion, perfusion, device fit, and other factors. The blood-oxygen guide is useful for understanding measurements after a clinician recommends monitoring—not for delaying emergency care.
When to seek emergency care
Call local emergency services now if the person has any of these signs:
- severe or rapidly worsening trouble breathing;
- stridor, harsh or high-pitched breathing, or visible effort to breathe;
- blue or gray lips, collapse, confusion, or inability to stay awake;
- inability to swallow saliva, marked drooling, or choking;
- rapidly increasing neck swelling;
- chest pain, fainting, a new irregular heartbeat, or severe weakness;
- new paralysis, trouble walking, altered speech, or difficulty moving the eyes;
- a child who is unusually still, exhausted, poorly responsive, or struggling to breathe.
Seek urgent same-day assessment for a suspected adherent throat membrane, a concerning sore throat after known exposure, or a compatible illness in someone whose vaccination is incomplete or unknown. Do not wait for every textbook feature or for a routine appointment several days away.
When you call, say that diphtheria is a concern and explain any close contact, recent travel, outbreak notice, skin wound, unpasteurized animal-product exposure, or incomplete vaccination. This helps the service choose a safe arrival route and notify infection-control and public-health teams.
What not to do while arranging care
- Do not scrape or pull at the membrane. Forced removal can make the attached tissue bleed and can destabilize an already narrow airway.
- Do not push a spoon, swab, finger, or camera deep into the throat. Sampling belongs in a clinical setting with airway support available.
- Do not take leftover antibiotics. The choice, dose, duration, cultures, and follow-up must be coordinated; unsupervised antibiotics can delay diagnosis and do not replace antitoxin for respiratory disease. Our antibiotics and microbiome guide covers broader reasons to avoid unnecessary use.
- Do not share cups, utensils, towels, bedding, or close face-to-face contact. Follow the health service’s isolation instructions rather than inventing a household protocol.
- Do not go unannounced into a crowded waiting room. Call first when the person is stable enough to do so; use emergency services immediately when breathing is threatened.
- Do not let vaccination history overrule dangerous symptoms. Vaccination greatly lowers the risk of toxin-mediated disease, but no symptom pattern should be dismissed solely because a record appears current.
Keep the person upright in the position that makes breathing easiest and avoid forcing food, drink, or pills when swallowing is difficult. Do not attempt steam treatments or throat sprays as a substitute for care.
Who is more likely to need diphtheria testing?
Diphtheria can occur in any nonimmune or under-immunized person. Clinical probability changes with context:
- incomplete, unknown, or outdated diphtheria vaccination;
- close household or habitual contact with a suspected or confirmed case;
- direct exposure to respiratory secretions or an infected skin lesion;
- travel to, or residence in, a community with active transmission or low vaccine coverage;
- overcrowding, disrupted health services, displacement, or barriers to routine immunization;
- occupational exposure in health care or laboratories;
- contact with animals or unpasteurized animal products when C. ulcerans is a local concern.
These factors do not diagnose the illness. A well-vaccinated person with ordinary viral symptoms is statistically more likely to have a common infection, while a compatible pseudomembrane and airway symptoms demand action regardless of probability. The correct threshold is clinical: could delay be dangerous?
Recent surveillance shows why “rare” does not mean “gone.” The ECDC annual epidemiological report for 2024 recorded toxigenic Corynebacterium infections in the EU/EEA, and the WHO continues to report outbreaks where vaccination gaps persist. Avoid stigmatizing travelers or displaced people; exposure assessment should support testing and vaccination, not blame.
How diphtheria is diagnosed
Diphtheria is first a clinical suspicion, then a laboratory confirmation. The sequence matters because waiting can let toxin bind to tissue.
Clinicians assess the airway and illness pattern first
The care team examines the nose, mouth, throat, neck, breathing, circulation, skin, neurologic function, and vaccination history. They ask when symptoms began, whether the coating has spread, which symptom appeared first, and whether there was close contact or travel.
The first priority may be protecting the airway rather than completing every test. Respiratory support, specialist airway management, and cardiac monitoring may be needed in severe disease. A normal respiratory-rate or wearable trend does not override stridor, drooling, or increasing effort; see our respiratory-rate guide for the limits of consumer measurements.
Culture identifies the organism; toxin testing establishes toxigenicity
When possible, clinicians collect throat, nasal, membrane, wound, or skin samples before antibiotics. A laboratory can culture Corynebacterium, but identifying the species is not the final step. Further testing determines whether the strain carries and expresses diphtheria toxin.
The CDC surveillance manual notes that polymerase chain reaction can detect the toxin gene, while a specialized test is needed to confirm toxin production. Public-health laboratories often coordinate this work. A negative early or post-antibiotic culture does not automatically erase a compelling clinical picture.
Treatment should not wait for confirmation when respiratory disease is suspected
Current CDC clinical guidance says presumptive therapy must begin quickly when the presentation supports respiratory diphtheria. Cultures should be collected first if that can happen without delaying treatment. This is why self-swabbing and waiting for an ordinary online test result are unsafe substitutes for urgent care.
How respiratory diphtheria is treated
Treatment is hospital- and public-health-led. It addresses toxin, bacteria, airway risk, organ complications, and transmission at the same time.
Diphtheria antitoxin neutralizes toxin that is still circulating
Diphtheria antitoxin (DAT) binds circulating toxin before it attaches to cells. It cannot reverse toxin already fixed to the heart, nerves, or other tissue. That biological limit explains why clinicians may give DAT on clinical suspicion rather than wait days for full laboratory confirmation.
DAT availability and access pathways differ by country. Clinicians obtain it through national or regional public-health authorities; it is not a retail medicine or preventive treatment for contacts. Because it is commonly derived from horse serum, trained teams assess allergy risk and monitor administration.
Antibiotics clear bacteria and reduce transmission
Antibiotics stop bacterial replication and further toxin production. The recommended agent depends on current national guidance, susceptibility, allergies, age, pregnancy, and clinical context. CDC guidance currently lists erythromycin or penicillin for respiratory and cutaneous disease, while other authorities may update regimens in response to resistance patterns.
Finishing treatment does not always prove that toxigenic bacteria are gone. Follow-up cultures can be required, and isolation continues according to clinical and public-health guidance. Never shorten a prescribed course because the throat looks better.
Airway, heart, and neurologic monitoring can be lifesaving
Extensive membrane or swelling can require airway support. Clinicians also watch for:
- myocarditis: rhythm disturbance, conduction block, heart failure, chest symptoms, or circulatory collapse;
- neuropathy: swallowing difficulty, eye-movement problems, limb weakness, or paralysis that can appear later;
- kidney injury: changing urine output or laboratory markers;
- secondary infection, poor nutrition, and deconditioning during recovery.
Antibiotics do not neutralize toxin that is already circulating, and antitoxin does not kill the bacteria. Both are used for respiratory toxin-mediated disease because they solve different problems.
What happens to household and close contacts?
Suspected or confirmed diphtheria triggers a public-health investigation. A close contact may include household members, people with habitual close face-to-face contact, and anyone directly exposed to secretions from the infection site.
Depending on local guidance, contact management can include:
- prompt symptom and exposure assessment;
- nose and throat cultures;
- preventive antibiotics even if the person feels well;
- review and update of diphtheria vaccination;
- temporary quarantine or activity restrictions;
- daily symptom monitoring and repeat testing.
Do not organize prophylaxis from another family member’s prescription. Public-health teams define who counts as a contact, which drug is appropriate, how long monitoring lasts, and when work, school, travel, or close contact can resume. If a contact develops sore throat, fever, neck swelling, a membrane, or breathing symptoms, they should report the exposure and seek care immediately.
Vaccination prevents severe toxin-mediated disease
Diphtheria toxoid vaccines train the immune system to neutralize toxin. They are usually given in combination with tetanus and pertussis vaccines, with a primary series and later boosters. The exact product, timing, catch-up schedule, pregnancy recommendation, and adult booster interval depend on age, medical history, travel, occupation, and country.
Three practical points matter:
- One childhood dose is not a lifetime series. Multiple primary and booster doses are needed for durable protection.
- Infection may not create reliable immunity. People recovering from diphtheria still need their vaccine status reviewed.
- Vaccination does not replace exposure management. Close contacts may need antibiotics, cultures, and an additional vaccine dose under public-health guidance.
Check an official national immunization schedule or ask a clinician or pharmacist to review the record. Older adults may have incomplete documentation or weaker immune responses; our immune aging guide explains that broader context, but it does not replace the country-specific vaccine schedule.
Community coverage matters as much as an individual record. High uptake reduces severe disease and limits the conditions in which toxin-producing strains can spread. Conflict, displacement, health-system disruption, and missed routine doses can reopen immunity gaps quickly.
Recovery can take longer than the throat illness
The visible membrane and fever may improve before the risk of delayed toxin complications has passed. Myocarditis can appear during the illness, while neuropathy and weakness may emerge later and persist for weeks or months. Follow the clinical team’s plan for heart rhythm checks, neurologic review, cultures, vaccination, nutrition, activity, and return to work or school.
Seek prompt reassessment for new palpitations, chest pain, fainting, breathlessness, swallowing difficulty, nasal speech, double vision, limb weakness, reduced urine output, or renewed fever. Return to exercise should be clinician-led after cardiac or neurologic involvement. A normal readiness score is not medical clearance.
Use SuperAge after clinical clearance—not during emergency triage
SuperAge cannot inspect a throat, secure an airway, diagnose diphtheria, arrange antitoxin, or manage contacts. If diphtheria is possible, call for care first and leave symptom logging for later.
During clinician-approved recovery, a short timeline of temperature, medication, sleep, resting pulse, symptoms, activity tolerance, and follow-up questions may help organize the handoff between hospital, primary care, and public health. Once the care team says personal tracking is appropriate, download SuperAge to keep that context together without treating a score as clearance.
FAQ
What are the first symptoms of diphtheria?
Respiratory diphtheria often begins gradually with sore throat, weakness, poor appetite, swollen neck glands, difficulty swallowing, and a low fever. A tough gray-white pseudomembrane may form over the tonsils, throat, or nose. Symptoms vary, so exposure and vaccination history matter too.
Is every gray or white coating in the throat diphtheria?
No. Common bacterial and viral infections, mononucleosis, candidiasis, abscesses, and other conditions can produce throat coatings or exudate. Color cannot diagnose the cause. An adherent membrane with swallowing difficulty, neck swelling, breathing symptoms, or relevant exposure needs urgent professional assessment.
Can I remove the diphtheria membrane at home?
No. The pseudomembrane is firmly attached, and forcible removal can cause bleeding. Manipulating the throat can also worsen distress or delay airway care. Do not scrape, swab, or pull it; call urgent medical services and follow their infection-control instructions.
Does diphtheria always cause a high fever?
No. Low-grade fever is more typical, and severe toxin-mediated illness can occur without a dramatic temperature. Worsening swallowing, breathing, neck swelling, weakness, or heart and neurologic symptoms matter more than one thermometer reading.
Can vaccination completely rule out diphtheria?
Vaccination greatly reduces the risk of severe toxin-mediated disease but does not make every infection impossible. Protection depends on a completed series and boosters, and schedules vary. Compatible emergency symptoms still need assessment regardless of the vaccination record.
Why do doctors treat diphtheria before test results return?
Antitoxin neutralizes circulating toxin but cannot undo toxin already attached to tissue. Waiting for culture and toxigenicity results can therefore reduce its benefit. Clinicians collect samples first when possible, then begin presumptive treatment when the clinical picture is concerning.
Do close contacts need treatment if they feel well?
Often, yes. Public-health guidance may require cultures, preventive antibiotics, vaccine review, quarantine or activity limits, and symptom monitoring. Asymptomatic people can carry and transmit the bacteria, so contacts should follow the official investigation rather than self-treat.
Key takeaways
- A tough gray pseudomembrane with sore throat, neck swelling, or swallowing difficulty is an urgent warning pattern.
- Do not touch or remove a suspected membrane; call ahead for urgent care and use emergency services for breathing difficulty.
- Diphtheria toxin can obstruct the airway and damage the heart, nerves, and kidneys even when fever is modest.
- Diagnosis uses the clinical pattern, culture, species identification, and toxin testing, but treatment may start before confirmation.
- Respiratory disease generally needs both antitoxin and antibiotics plus airway and organ monitoring.
- Close contacts require public-health-led evaluation, prophylaxis, cultures, and vaccination review.
- A complete vaccine series and boosters are the strongest prevention; use the official schedule for your country.
References
- World Health Organization. Diphtheria fact sheet. Updated July 15, 2026.
- Centers for Disease Control and Prevention. Diphtheria symptoms and complications. Updated May 12, 2025.
- Centers for Disease Control and Prevention. Clinical overview of diphtheria. Updated May 12, 2025.
- Centers for Disease Control and Prevention. Clinical guidance for diphtheria. Updated May 12, 2025.
- Centers for Disease Control and Prevention. Manual for the surveillance of vaccine-preventable diseases: diphtheria. Updated January 2, 2025.
- Centers for Disease Control and Prevention. Pink Book, chapter 7: diphtheria. Reviewed April 10, 2024.
- UK Health Security Agency. Public health control and management of diphtheria in England: 2025 guidelines. Updated July 17, 2025.
- European Centre for Disease Prevention and Control. Annual epidemiological report for 2024: diphtheria. Published 2026.
- Truelove SA, Keegan LT, Moss WJ, et al. Clinical and epidemiological aspects of diphtheria: a systematic review and pooled analysis. Clinical Infectious Diseases. 2020;71(1):89–97.
This article is for general education and does not replace emergency assessment, public-health instructions, vaccination advice, or individualized medical care. If diphtheria is possible, seek urgent in-person care and avoid close contact until professionals advise otherwise.
Related Articles

How to ride a mountain bike: beginner technique guide
Learn how to ride a mountain bike with safer body position, braking, cornering, climbing, line choice, trail drills, and a clear beginner progression.

